


I went to more sessions at AIDS 2026 in Rio than I can count. The one I keep thinking about was a one-hour satelitte session organized by the Clinton Health Access Initiative (CHAI). Katherine Guerra opened it. Then Sulaiman Lakoh of Sierra Leone, Stephen Macheso of Malawi, Vichea Ouk of Cambodia and Gerald Nyamutamba of Zimbabwe talked about how they are keeping HIV programs running as aid declines.
The disconnect was hard to miss.
In Washington, much of the conversation is about protecting and preserving what PEPFAR built. And for good reason, don’t get me wrong. But In countries, the conversation has already moved on. It is about adapting programs, building new protections and deciding what can survive a very different funding future. And I think that is a good thing.
The conversation was practical and specific. They talked about rewriting clinical guidelines, consolidating supply systems, shifting costs onto national budgets and keeping skilled workers in place as donor-funded positions disappear. They were also clearly already making hard decisions about which services to protect first.
Some of the mitigation strategies were remarkable. Others left me uneasy. More about that below.
There were clear warnings about the lack of resources to expand prevention with anything close to the ambition this moment requires. I also heard blind spots around the last mile, especially the interventions needed to reach people at highest risk of acquiring HIV. Those are early warning signs. We should treat them that way.
Let me also be clear about what I mean by “post-PEPFAR.” PEPFAR is not over. Its job is not done. The latest UNAIDS data show that in 2025 the world recorded one million more new HIV infections and 400,000 more AIDS-related deaths than it would have if we were on track to meet global targets. PEPFAR remains critical even if it’s a shell of its former self.
So what are countries doing?
A view from five countries
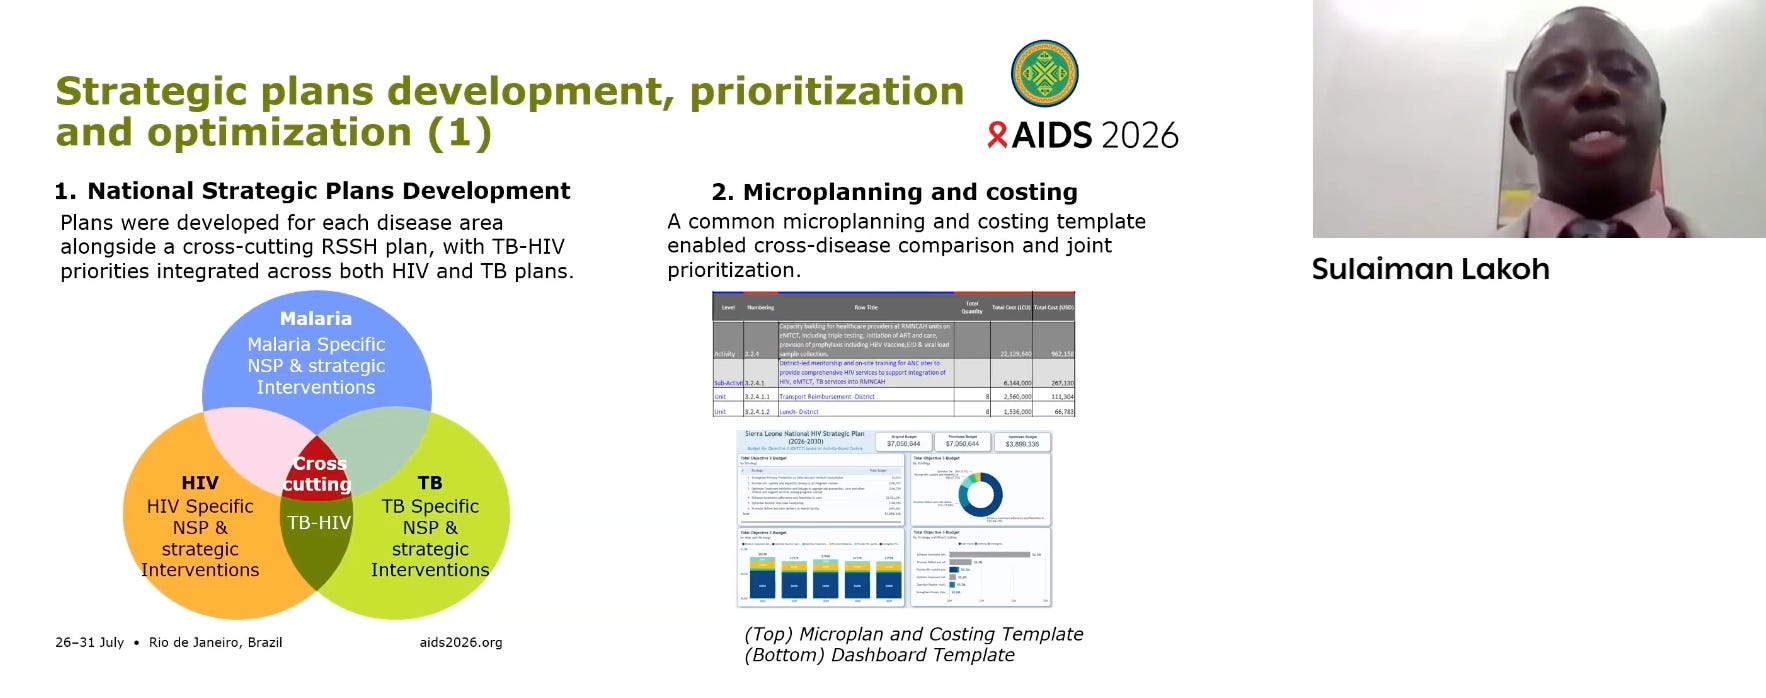
Sierra Leone. Sulaiman Lakoh described how the country is using the funding squeeze to integrate HIV, tuberculosis and malaria more deliberately into primary care. It is aligning plans, costing, laboratories, supply chains, financing and data across 13 shared areas.
Malawi. Stephen Macheso walked through the country’s effort to simplify its national HIV guidelines. That includes reducing the number of antiretroviral therapy initiation regimens from 15 to 3 and reconsidering how often stable patients need viral load testing.
Cambodia. Vichea Ouk described a country that has achieved more than 98 percent viral suppression among people on treatment. But new infections continue, especially among key populations. Its next challenge is sustaining treatment while financing a much more ambitious prevention response.
Zimbabwe. Gerald Nyamutamba focused on the nuts and bolts: forecasting, procurement and data visibility. Better quantification has reduced stockouts and expiries and produced about $96,720 in monthly savings.
Zambia. Earlier in the week (not part of this session), Lloyd Mulenga described a minimum package for sustainable HIV service delivery across 2,885 facilities. It sets a common standard. It also forces hard choices about what to continue, what to integrate and what to stop.
None of these countries has figured it all out of course. That is partly what made the presentations so useful. They offered an honest look at decisions being made in real time.
Here are four themes that emerged for me:
Integration as a sequence
Integration is not one decision. It is a series of decisions about services, money, workers, commodities, laboratories, data and accountability.
Each function moves at a different speed. Each carries a different risk if it fails.
Lakoh was explicit about that. Because roughly 80 percent of services in Sierra Leone are delivered through primary care, the government is redesigning programs around the place where people already receive care. It is also using common planning and costing tools to rank interventions. Its goal is to increase domestic financing for HIV from 9 percent to 20 percent by 2030.
Mulenga showed how Zambia is approaching the same challenge through its minimum package (see figure below). The government is establishing a consistent floor for HIV services while weighing what it can afford and how it will hold the system accountable.

This is what country ownership looks like: a government deciding what to integrate, how community-led services fit within the national system, what to protect and what it can realistically sustain. But integration is not a single handoff. It is a managed sequence. Some services may move into primary care quickly. Procurement, laboratories, community workers and commodity financing will take longer. Rushing that process does not make transition happen faster. It simply makes disruption more likely and harder to detect.
Efficiency and its risks
Efficiency is one of the most overused words in global health. Too often, it means doing the same work with fewer people until something quietly breaks.
That was not what Stephen Macheso described in Malawi. The country is reviewing its HIV clinical guidelines line by line to remove unnecessary complexity. That work includes reducing the number of antiretroviral therapy initiation regimens from 15 to 3 and reconsidering how frequently stable patients need viral load testing.
Those changes have practical consequences. Fewer regimens mean fewer products to forecast, procure and keep on clinic shelves. They also simplify training and make it easier for health workers to follow the guidelines consistently. Done well, simplification can lower costs while making care easier to deliver.
But Macheso drew an important line. Simplification is not the same as cutting services indiscriminately. Each proposed change had to preserve quality, equity and health outcomes. When the evidence did not support a proposal, officials reconsidered it. A process expected to take six months had already taken more than a year. See here:

The delay was worth it because Malawi was asking whether each proposed change would actually improve the program, not simply save money.
Lloyd Mulenga made the tradeoffs more explicit in Zambia. Generalized community HIV testing is being replaced with more targeted approaches designed to produce higher yield at lower cost. Prevention for adolescent girls and young women (formerly DREAMS) is being integrated into youth-friendly services instead of operating as a parallel platform. See full list below.

These choices may make sense on paper (or a slide for that matter) but they can also create new gaps. More targeted testing may produce better numbers while missing people whose risk is less visible. Integration may reduce duplication while weakening the community services that reached people the formal system never did.
The prevention warning
Cambodia has extraordinary treatment outcomes. Yet new infections continue, and prevention remains heavily dependent on external financing.
Treatment is easier to defend as an essential obligation. Prevention is more exposed. That is especially true when it is delivered through community organizations serving gay men, sex workers, people who use drugs and others pushed to the margins.
Ouk described Cambodia’s joint HIV and tuberculosis sustainability roadmap. The country is absorbing more commodity costs into the national budget and examining how twice-yearly injectable lenacapavir might fit into its prevention strategy.

Mulenga described Zambia as narrowing prevention rather than abandoning it. But the shift from broad community testing to more targeted approaches raises a basic question: who becomes harder to find?
Long-acting PrEP should be available to anyone who wants it and could benefit from it, across all populations at risk of acquiring HIV. Targeting can help programs reach people, but it should not become a barrier that determines who gets access to new prevention options.
I worry that the current financing conversation is much better developed around treatment continuity than around the prevention ambition needed to keep epidemics moving downward. Treatment continuity is non-negotiable. But if prevention becomes a causality of aid transition, new infections will rise again.
Data should govern the transition
Gerald Nyamutamba’s presentation on Zimbabwe focused on the basic workings of the supply chain: forecasting, procurement, warehouses and the movement of data between facilities and the central government.
A 2025 assessment found experienced supply-chain staff, but weak interoperability and limited visibility across the system. Zimbabwe responded by combining forecasting across disease programs, creating a Ministry of Health-led procurement and supply management group, and linking facility and central systems through its digital health blueprint. Nyamutamba reported fewer stockouts and expired products, along with about $96,720 in monthly savings.
Other countries described using data in similar ways. Zambia’s minimum package provides a benchmark for assessing service quality. Malawi reviewed the evidence behind each proposed guideline change and rejected changes that could not be supported. Sierra Leone is using shared planning and costing tools to compare interventions and decide what to prioritize.
These examples show why data needs to guide the pace of transition. Governments and donors need to know whether integration is improving services, creating new gaps or weakening access for particular communities.
A July 2026 National Academies report commissioned by the U.S. State Department recommends tracking viral suppression, retention in care, commodity availability, service quality and access throughout the process. If those indicators begin to deteriorate, governments and donors should be prepared to slow, revise or reverse parts of the transition.
What Washington needs to hear
If you have read this far, you probably understand why this session stayed with me. Country after country described practical changes already underway. This is not the conversation we are having in Washington. It should be.
Country realities should be the starting point for transition. Integration needs to happen function by function, with evidence guiding what moves, what stays and what needs more time. Simplification can reduce costs, but it cannot come at the expense of quality or access. And workforce, community delivery, prevention, supply chains and data systems cannot be treated as secondary concerns.
Country agreements should start with the plans governments are already building. Timelines should reflect how long implementation actually takes. Donors also need to fund the transition itself. Integration costs money. So does retaining critical staff and protecting services that domestic budgets cannot absorb overnight.
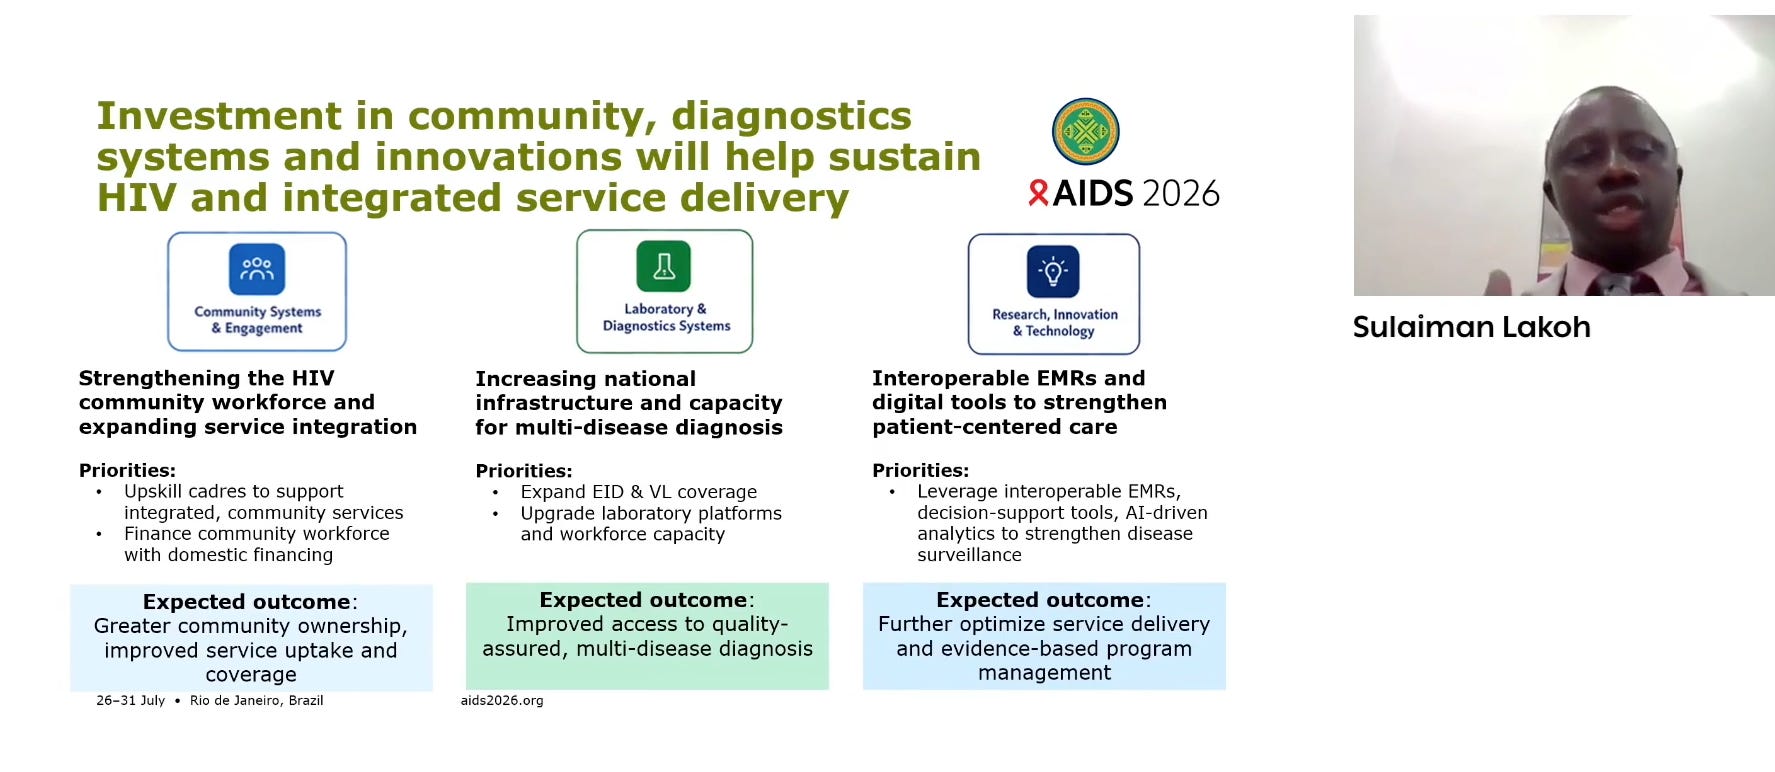
The National Academies report is clear on this point. Integration is not a substitute for adequate investment. Moving HIV services into primary care without realistic costing, protected budgets and procurement capacity risks creating an unfunded mandate.
One final thought - I was keen to see how governments are beginning to use AI to strengthen efficiency planning and improve service delivery. I am eager to learn more about what is working and how these tools can be scaled responsibly.
CHAI should take this session on the road. The officials shaping PEPFAR agreements in Washington, Global Fund decisions in Geneva and aid budgets across Europe need to hear directly from the people managing these choices.
I left Rio impressed by how quickly countries are adapting but also worried about the limits of what adaptation can achieve. Countries cannot compensate indefinitely for declining resources, especially if prevention, community delivery and the last mile are treated as optional.
A note to readers
Washington still sets much of the policy and controls much of the money. But country voices need to be much closer to the people making those decisions. That is hardly a new idea, yet somehow we have lost the plot on it.
I want to work with others committed to bringing evidence-based country stories directly to lawmakers, the State Department and other donor capitals. If that sounds like you, please reach out to me.
Excellent post. I'm reasonably optimistic that the US will not fully abandon HIV, TB, Malaria and disease surveillance/outbreak control and the Global fund will continue albeit at a reduced level. Focused donor programming, country led simplification and modest investment, and safety nets for unforeseen shocks can get us through.